Cervical spondylosis is the medical term for wear and tear of the discs and small joints in the neck. Like grey hair, it is part of normal ageing. Most people with it have no symptoms or only occasional neck stiffness, but in some it causes persistent neck pain or begins to press on nerves or the spinal cord.

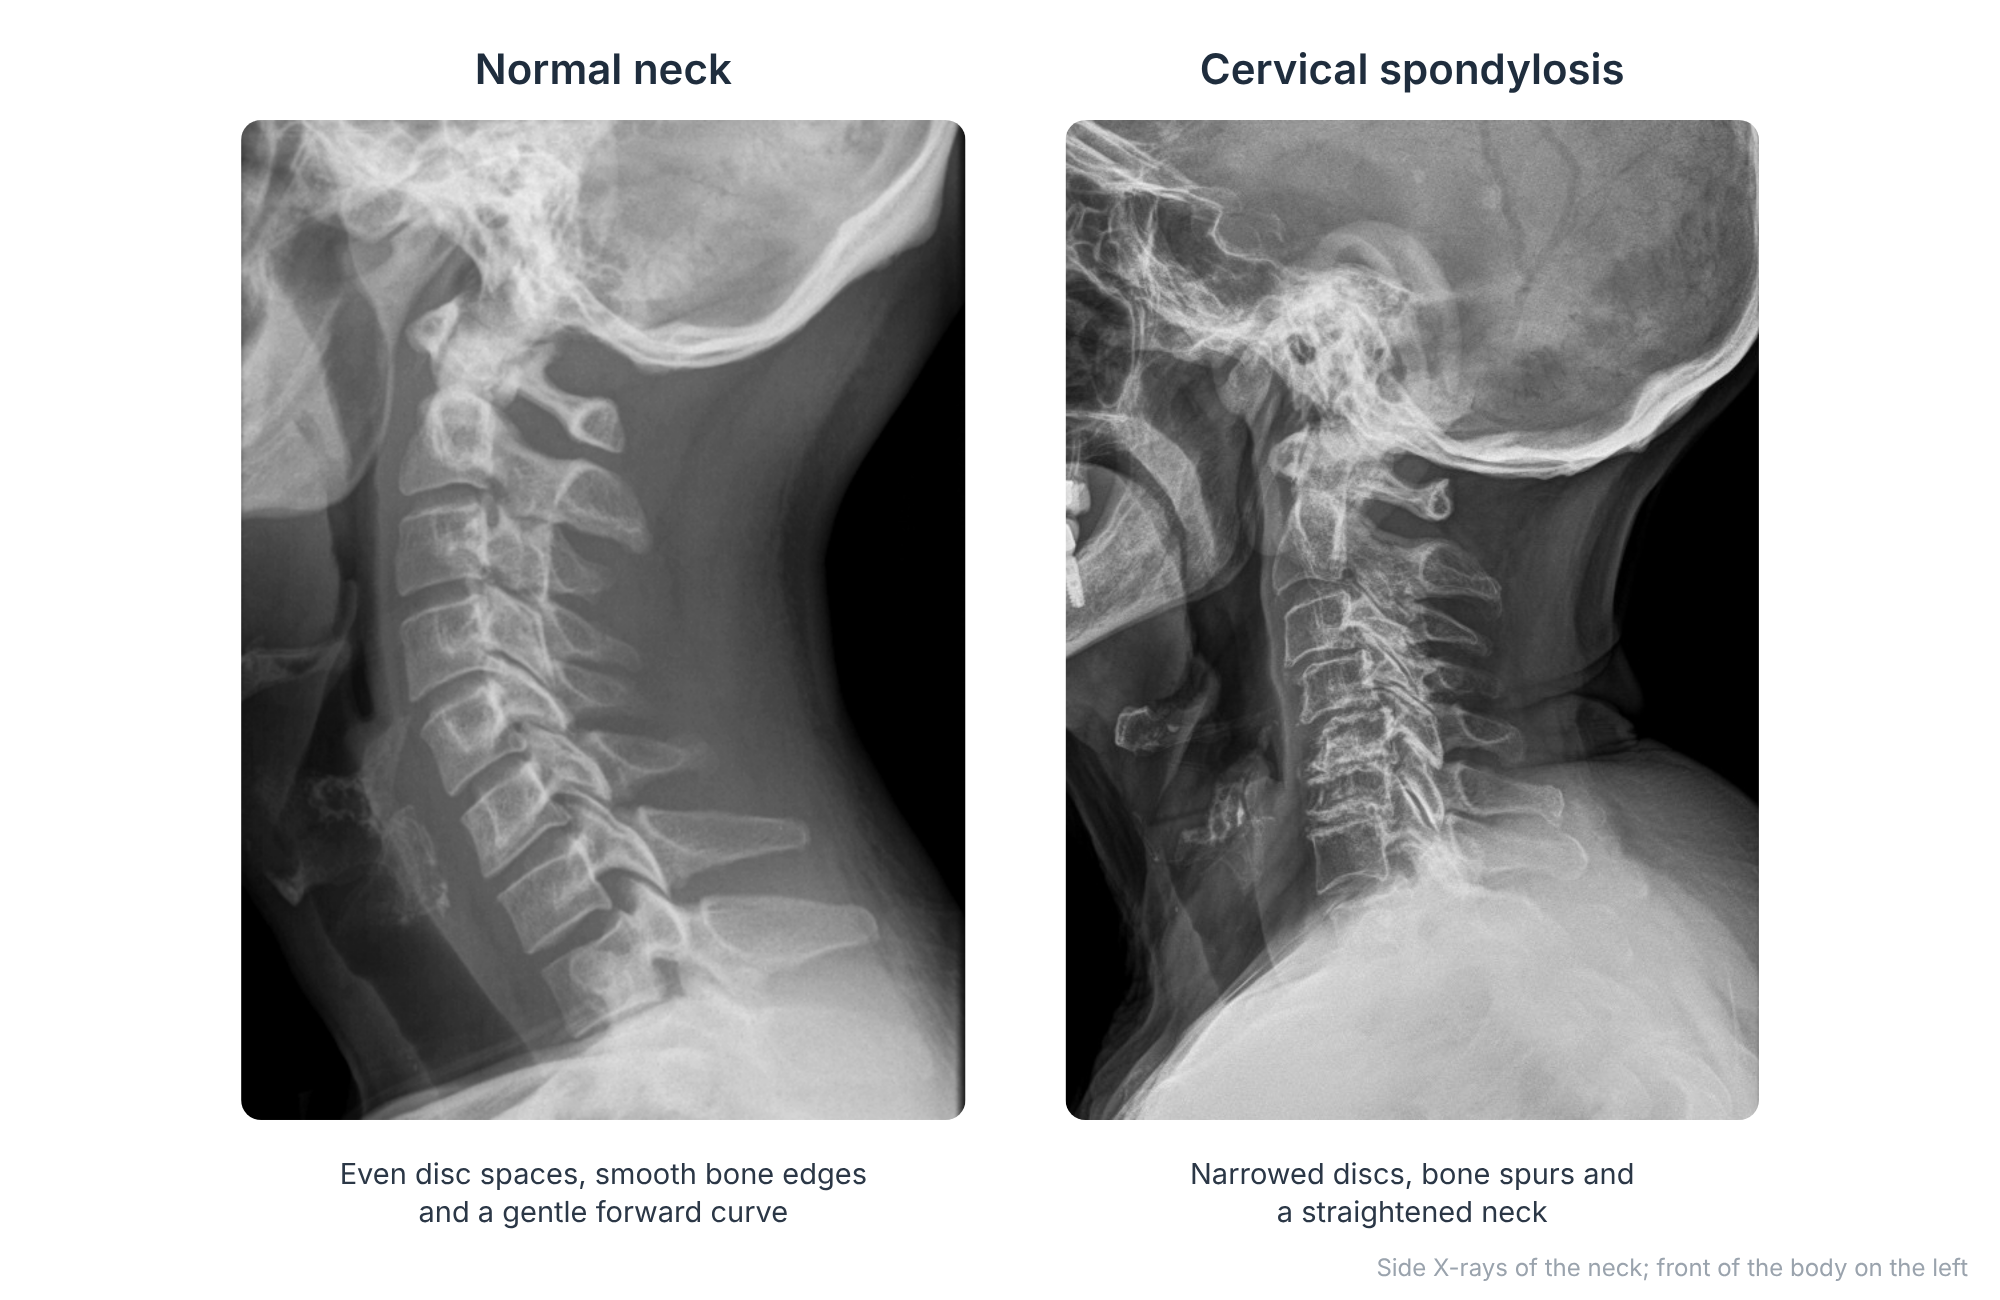
At a glance
- Over 85% of people over 60 show degenerative changes on neck MRI, often without any symptoms.
- Most episodes of neck pain improve substantially within 6 to 8 weeks, whatever treatment is used.
- Surgery is rarely recommended for neck pain alone.
- It becomes more important if bone spurs or discs pinch a nerve (radiculopathy) or the spinal cord (myelopathy).
Symptoms
- Neck pain and stiffness, often worse in the morning or after long periods at a desk or screen.
- Pain spreading to the shoulder blades or the base of the skull, sometimes with headaches.
- Grinding or clicking sensations when turning the head.
- Warning signs that nerves are involved: pain, tingling or weakness in an arm. Warning signs that the spinal cord is involved: clumsy hands, difficulty with buttons or handwriting, or unsteady walking. These need specialist review.
Risk factors
- Age, the main factor.
- Genetics.
- Occupations involving repetitive neck movement, heavy overhead work or prolonged static postures.
- Previous neck injury, such as whiplash or contact sport injuries.
- Smoking.
How is it diagnosed?
Clinical assessment is the most important step. X-rays show disc height, bone spurs and alignment. MRI is recommended if there are arm symptoms, signs of spinal cord involvement, or pain that does not settle.
Non-surgical treatment
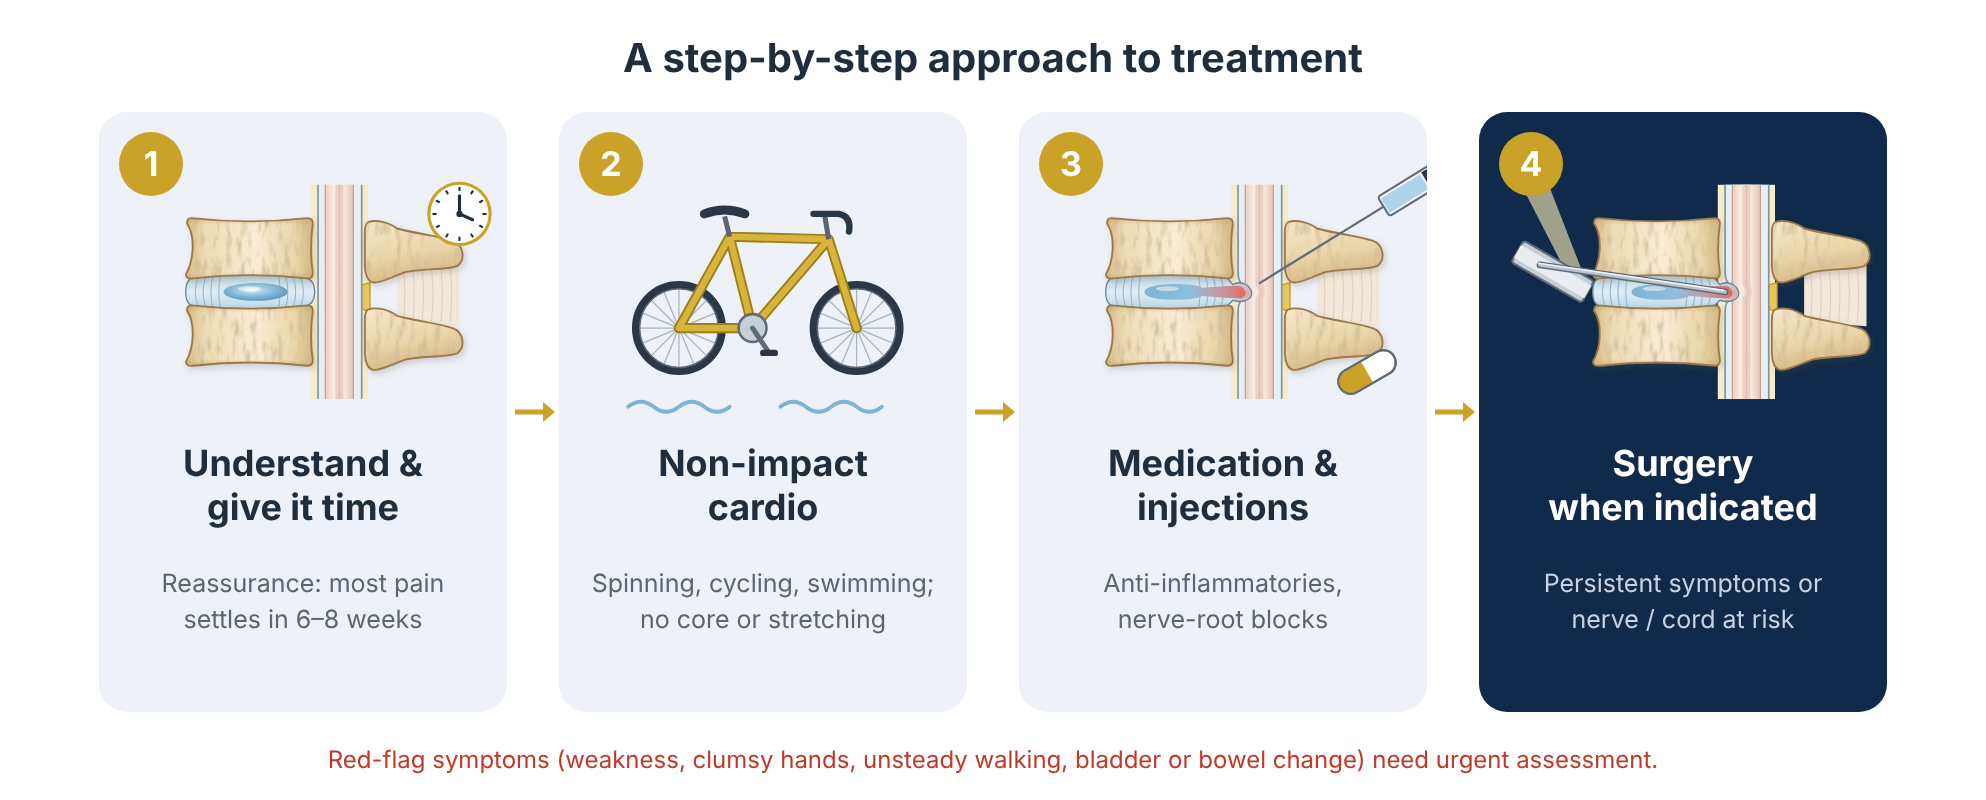
- Non-impact cardio: regular cycling, spinning or swimming (choose a stroke that doesn’t hurt your neck) for fitness and pain relief. Neck stretching and strengthening programmes are not needed and may aggravate stiff, worn joints. See Spinal health and common sense.
- Physiotherapy, massage or manual therapy can give comfort and reassurance while the pain settles, although they have not been shown to beat natural recovery.
- Workstation comfort: sensible screen height and regular breaks if they help. Special chairs, pillows and supports have not been shown to prevent neck or back problems.
- Medication: short courses of anti-inflammatories or simple analgesics.
- Facet joint injections or radiofrequency denervation for persistent pain from the small joints of the neck.
- Soft collars are not recommended for routine neck pain because they encourage stiffness.
Surgical options
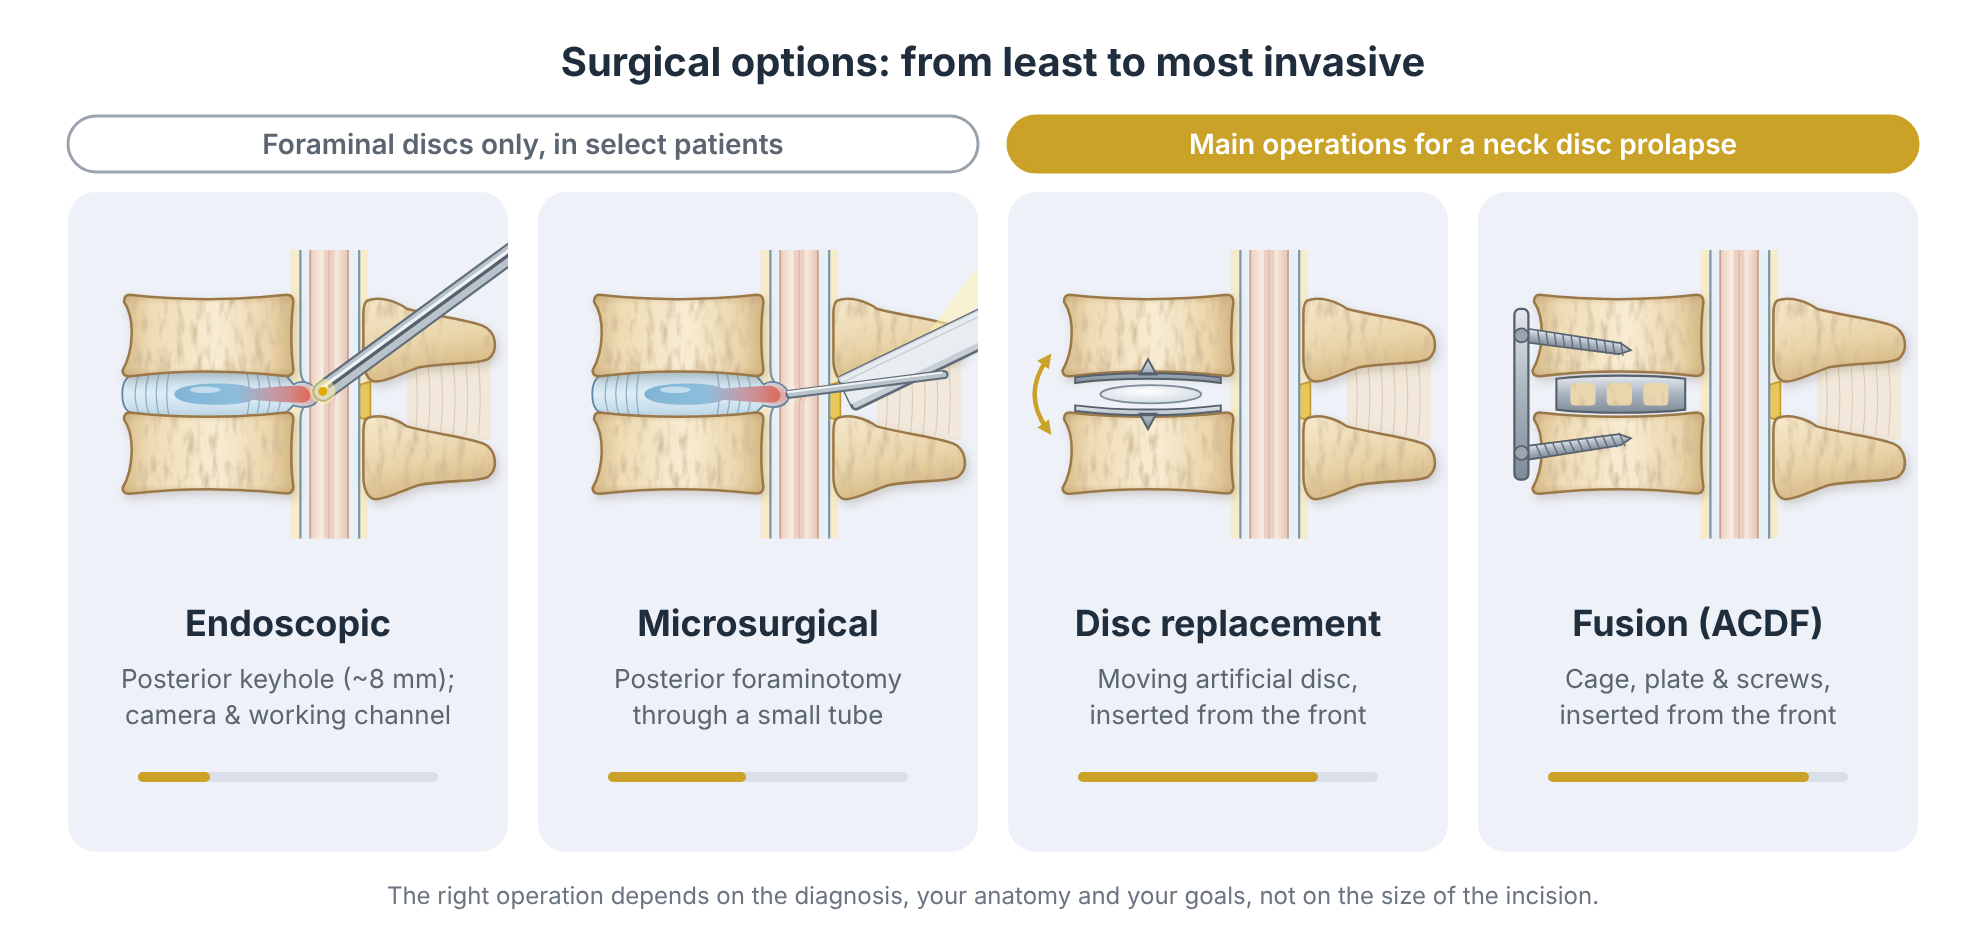
Surgery is considered when degeneration compresses nerves or the spinal cord. For neck pain alone, the evidence for surgery is weak, and it is reserved for rare, carefully selected cases.
Endoscopic and minimally invasive surgery
Posterior endoscopic or microscopic foraminotomy enlarges the exit hole for a pinched nerve without fusion. It is only suitable for a foraminal disc prolapse (one pressing on the nerve where it leaves the spine), in select patients (see cervical radiculopathy).
Anterior cervical discectomy and fusion (ACDF)
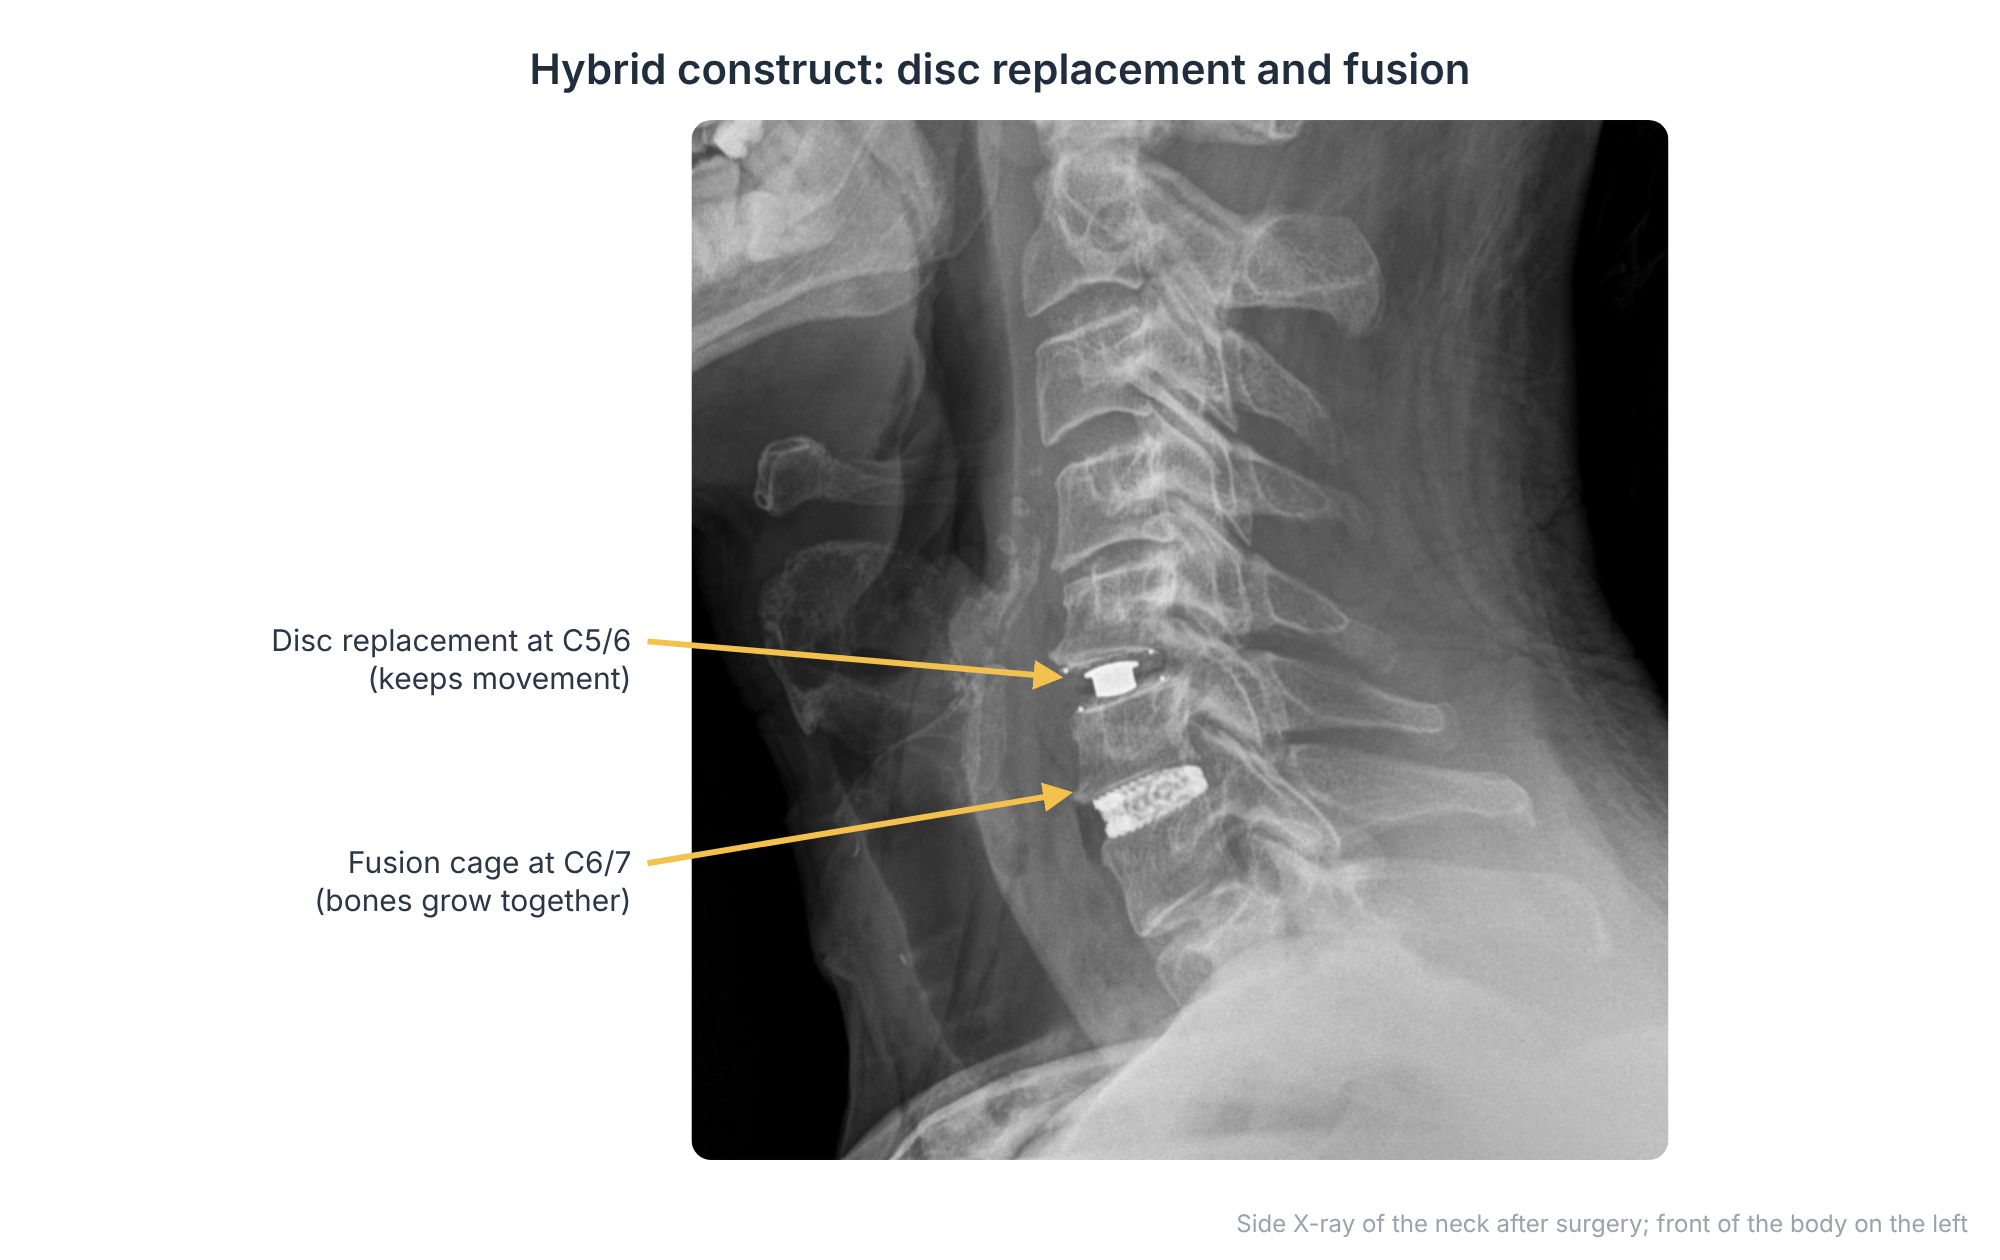
Through a small incision at the front of the neck, the worn disc and spurs are removed and replaced with a spacer, often secured with a small plate. It is one of the most successful operations in spinal surgery when the problem is nerve or cord compression.
Cervical disc replacement
An artificial disc is used instead of a fusion to preserve movement. It is best suited to younger patients with one or two affected discs and healthy facet joints.
Posterior decompression and fusion, or laminoplasty
These are used when several levels are involved, usually for spinal cord compression (see cervical myelopathy).
What the evidence says: Neck pain and imaging
A Japanese study of 1,211 people without symptoms (Nakashima and colleagues, Spine 2015) found disc bulging on MRI in about 88%. Degenerative changes on a scan therefore need to be interpreted alongside the clinical findings. A Cochrane review found that exercise programmes reduce pain and improve function in chronic neck pain.
Outlook
For most people, cervical spondylosis causes intermittent symptoms that can be well controlled with exercise and good habits. Regular review is advisable if you notice any arm symptoms, hand clumsiness or balance problems.
Talk to Prof Kruger
If you are living with this condition and would like an opinion on your options, you are welcome to book a consultation. Please bring any recent scans and reports.
References and key studies
- Nakashima H, et al. Abnormal findings on magnetic resonance images of the cervical spines in 1211 asymptomatic subjects. Spine. 2015;40(6):392–398.
- Gross A, et al. Exercises for mechanical neck disorders. Cochrane Database Syst Rev. 2015;(1):CD004250.
- Hurwitz EL, et al. Treatment of neck pain: noninvasive interventions. Results of the Bone and Joint Decade 2000–2010 Task Force on Neck Pain and Its Associated Disorders. Spine. 2008;33(4 Suppl):S123–S152.
- Carragee EJ, et al. Treatment of neck pain: injections and surgical interventions. Results of the Bone and Joint Decade 2000–2010 Task Force on Neck Pain and Its Associated Disorders. Spine. 2008;33(4 Suppl):S153–S169.
This page is general patient education based on published research and is not a substitute for a personal consultation. Treatment is always tailored to the individual.